

No one knows, and anyone giving you a percentage is guessing.
Medicare accreditation and software selection are unrelated processes. CMS requires DMEPOS suppliers to be accredited by a CMS-approved accreditation organization in order to enroll in and bill Medicare (CMS, DMEPOS Accreditation Organizations). Accreditation organizations survey your business practices, your product-specific service standards, and your documentation. None of them require, endorse, or record a software platform. CMS doesn’t collect it either. There is no field for it in PECOS, and no public file that reports it.
The market-share figures you’ll find in search results trace back to two sources: a 2014 trade magazine article, and vendor marketing copy in a buyers’ guide. Neither has been updated in a decade, and neither was ever independently audited.
What can be said honestly
Brightree, owned by ResMed, is the most widely deployed platform in US HME/DME by a wide margin. That’s observable — it’s the system most suppliers name when they describe what they’re migrating from, it’s the platform every competitor benchmarks against, and it has the broadest integration ecosystem in the category. “Most widely deployed” is defensible. “Used by 40% of accredited suppliers” is not.
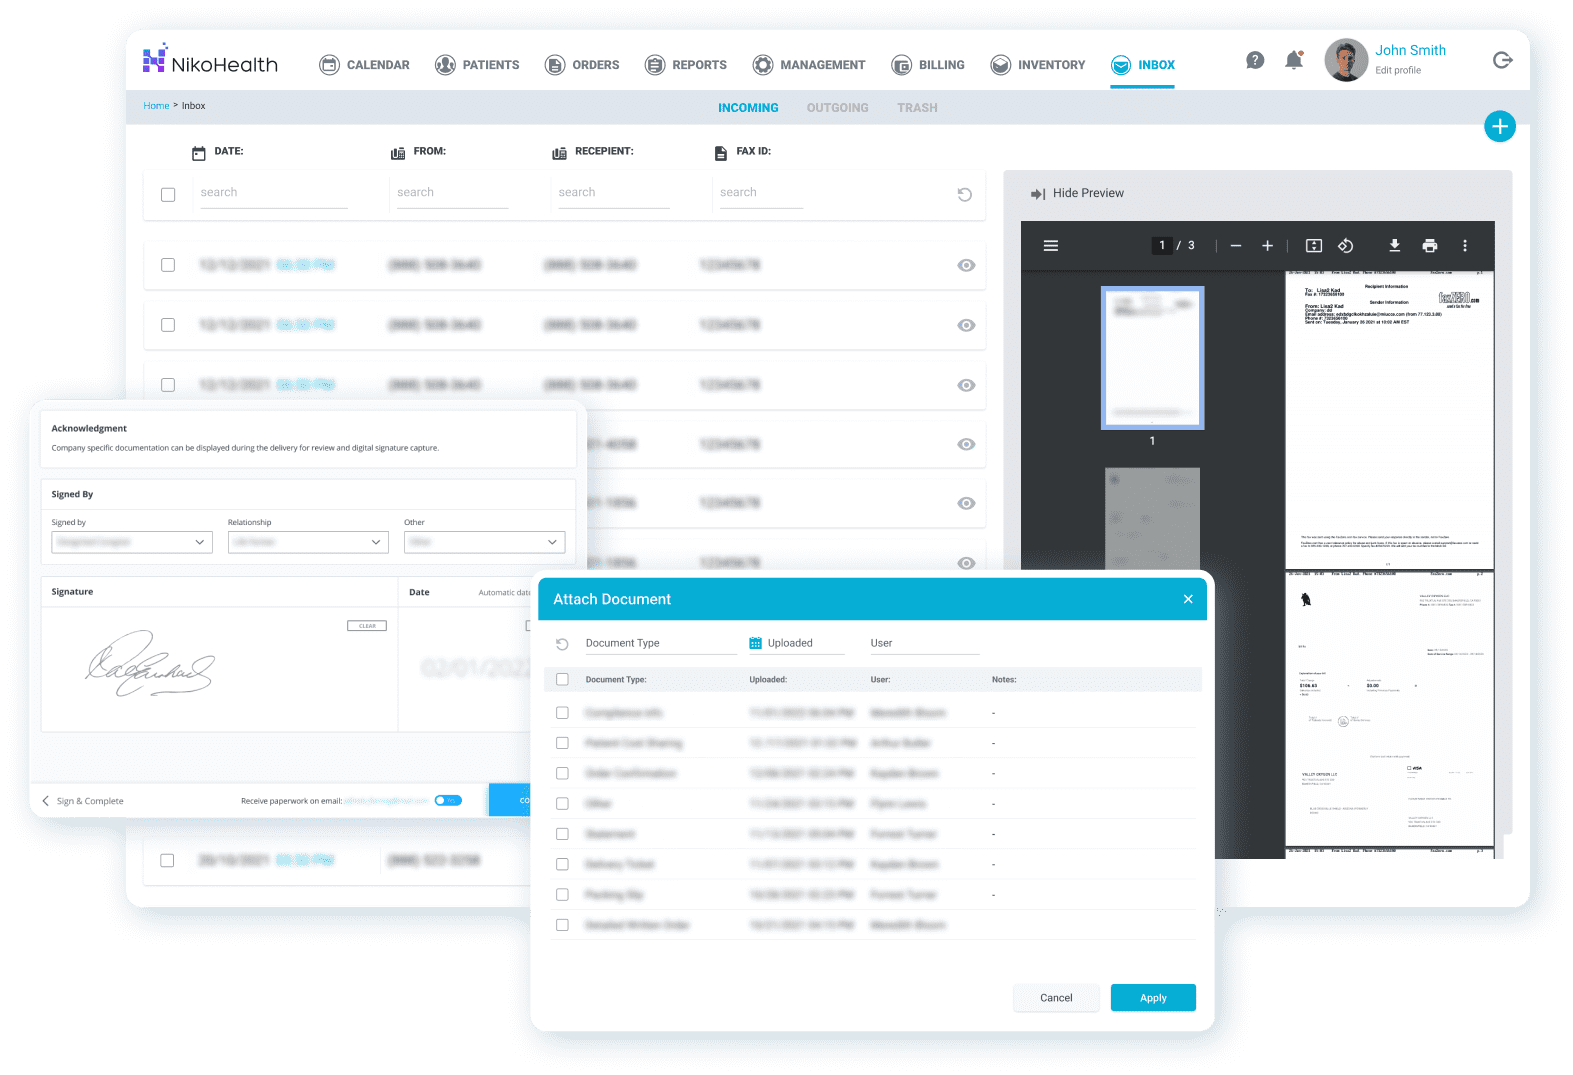
NikoHealth sits at the other end of that axis. Founded in 2018 and built cloud-native from the start, it wasn’t migrated to the cloud from a desktop product — the architecture assumed it. That shows up in the AI layer: AI Routing for delivery, Voice AI for resupply outreach, and AI-assisted patient entry at intake. A platform architected around an open API in 2018 can add them; a platform architected around a desktop install in 1998 has to bolt them on.
Beyond those, the field is fragmented: Bonafide (WellSky), TIMS Software (Computers Unlimited), WellSky CareTend, Nymbl Systems, Curasev, DMEworks, TeamDME!, Fastrack, and others. No single one holds a share anyone has credibly measured.
Why this question usually isn’t the real question
Suppliers ask “what does everyone else use” as a proxy for “what’s safe.” That proxy has gotten less reliable, not more. Accreditation is the reason.
Under the CY2026 Home Health PPS final rule, CMS shortened the DMEPOS survey and reaccreditation cycle from at least every 36 months to at least every 12 months, effective January 1, 2026. Suppliers who could previously reconstruct documentation on a three-year rhythm are now being surveyed annually. What matters for accreditation isn’t which logo is on your software. It’s whether the system can produce, on demand, the proof of delivery, the standard written order, the beneficiary instruction record, and the audit trail showing who touched what and when.
Ask a different question of any vendor: show me how you’d respond to an accreditation survey using only what’s in this system. A platform that can answer that is a safe choice regardless of how many other suppliers use it. A platform that can’t is a risk no market share protects you from.



